PCOS in Nigeria: Symptoms, Treatment and Fertility
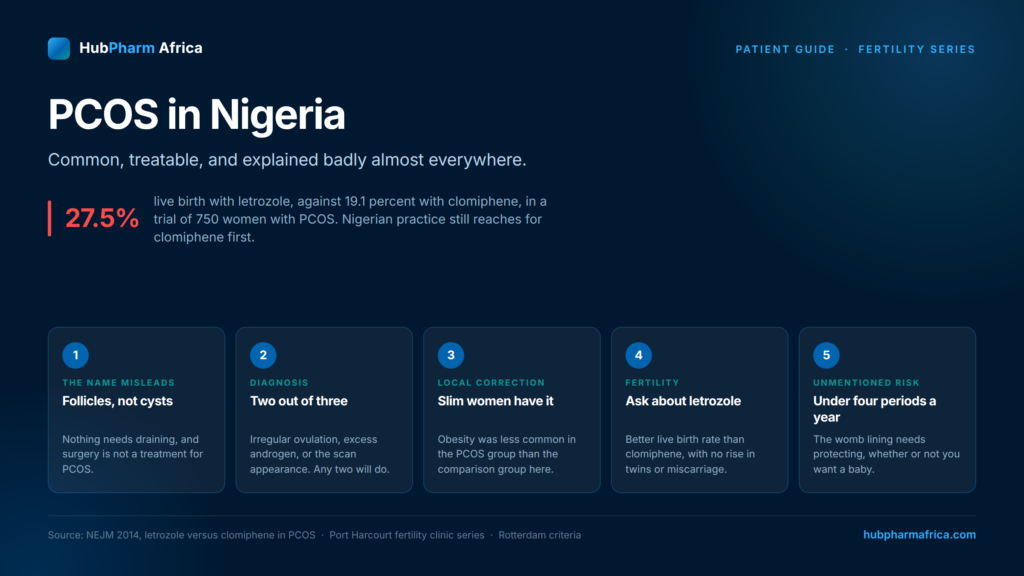
Most women reach this page after a scan report says “polycystic ovaries” and nobody explains what that means. Then comes a search, a frightening list, and a suggestion from somewhere that surgery will fix it.
PCOS in Nigeria is common, treatable and badly explained. This guide covers how doctors actually diagnose it, which medicine now works best for fertility, why the condition matters even when you are not trying to conceive, and one period-related risk that almost nobody here mentions.
What PCOS in Nigeria looks like
PCOS in Nigeria presents exactly as it does elsewhere, and it gets explained far worse. Polycystic ovary syndrome is a hormonal condition, not an ovarian disease. The ovaries make more androgen than usual, ovulation becomes irregular or stops, and insulin often works less efficiently than it should.
In a study of 174 infertile women at a fertility clinic in Port Harcourt, 16.7 percent had PCOS by Rotterdam criteria, with a mean age of 33.
| Feature | Women with PCOS | Women without |
| Infrequent periods | 27.5% | 2.4% |
| Excess hair growth | 55.2% | 12.6% |
| Acne | 43.1% | 31.5% |
| Obesity | 12.8% | 29.1% |
Look carefully at that last row, because it contradicts what most people believe about PCOS in Nigeria.
How PCOS in Nigeria is diagnosed

Two out of three
Doctors use the Rotterdam criteria, which need any two of these three.
- Irregular or absent ovulation, usually showing as infrequent or missing periods
- Excess androgen, either visible as unwanted hair, acne or scalp thinning, or measurable on a blood test
- Polycystic appearance of the ovaries on ultrasound
Because only two are needed, plenty of women have PCOS with entirely normal-looking ovaries, and plenty of women with that scan appearance do not have the syndrome at all.
Your doctor should also exclude thyroid disease, raised prolactin and other causes first, since all of them imitate PCOS in Nigeria closely enough to fool a quick consultation.
The ovaries do not contain cysts
The name causes real distress and occasionally real harm. Those small round structures on the scan are follicles, meaning immature eggs, not cysts.
Therefore nothing needs draining, and surgery is not a treatment for PCOS in Nigeria or anywhere else. Anyone offering to remove them for a fee is selling you something you do not need.
You do not have to be overweight
Here is the local correction that matters most.
In that Port Harcourt series, obesity was less common among the women with PCOS than among the women without it. Slim Nigerian women get told they cannot have PCOS, so they go undiagnosed for years while their periods stay irregular.
Weight is a risk factor, and weight loss helps those who carry extra. Nevertheless, a normal body weight never rules the diagnosis out.
Treatment for PCOS in Nigeria, when you are trying to conceive
Letrozole comes first now
This is the single most useful sentence on the page.
A trial of 750 women with PCOS compared letrozole against clomiphene for ovulation induction. Live birth occurred in 27.5 percent of the letrozole group against 19.1 percent of the clomiphene group, a statistically significant difference, with no significant difference between the groups in miscarriage, twin pregnancy or birth defects.
International guidance has followed that evidence and now places letrozole first for ovulation induction. Yet treatment for PCOS in Nigeria frequently still starts with clomiphene, largely out of habit.
So if you have PCOS and your doctor is starting ovulation induction, it is entirely reasonable to ask whether letrozole would suit you better. Ask the question rather than switching anything yourself.
Clomiphene still has a place
Clomiphene works for many women and remains widely used. The clomiphene article covers its risks in detail, and one point belongs here too.
Neither drug should be taken without ultrasound monitoring. Unmonitored ovulation induction raises the chance of twins and triplets substantially, and a triplet pregnancy carries serious risk for mother and babies. Both are prescription medicines for exactly that reason.
Metformin improves how the body handles insulin, and it helps some women ovulate. It works best for the metabolic side of PCOS in Nigeria rather than as a standalone fertility drug, and guidance generally places it behind letrozole for conception.
Start low, take it with food, and expect the stomach upset to settle. The metformin article explains that in full.
If ovulation induction does not work
Next steps include adding gonadotrophins under close monitoring, laparoscopic ovarian drilling in selected cases, or IVF. Your clinic decides the order.
PCOS in Nigeria is a lifelong condition, not only a fertility one
Women get discharged from fertility care after a successful pregnancy and never hear about PCOS in Nigeria again. That is a mistake, because the metabolic part does not go anywhere.
Type 2 diabetes. Insulin resistance sits at the centre of PCOS, and the risk of developing type 2 diabetes is substantially higher than in women without it. Ask for a fasting glucose or HbA1c, and repeat it periodically.
Blood pressure and cholesterol. Both deserve checking yearly, because cardiovascular risk factors cluster in this group.
Sleep apnoea. Snoring with daytime exhaustion is worth mentioning to a doctor rather than ignoring.
Mood. Rates of anxiety and low mood run higher in women with PCOS, and that is a consequence of the condition rather than a character flaw.
The period problem nobody mentions
Read this section even if you are not trying to conceive, because it is the part of PCOS in Nigeria that goes unmanaged for a decade at a time.
When ovulation does not happen, the womb lining keeps thickening under oestrogen without the progesterone that normally sheds it. Over years, that unopposed thickening raises the risk of endometrial hyperplasia and endometrial cancer.
The practical rule is simple. If you are having fewer than about four periods a year, tell a doctor. Options include a course of progestogen every few months, a combined pill, or a hormonal intrauterine device, all of which protect the lining.
Many Nigerian women treat absent periods as a blessing, or as something to worry about only when they want a baby. Consequently this risk goes unmanaged for a decade at a time.
Hair, skin and weight
Unwanted hair. Combined oral contraceptives reduce androgen effects over months, and anti-androgens such as spironolactone help further, although they require reliable contraception because they can harm a developing baby. Cosmetic treatments work alongside medicine rather than instead of it.
Acne. Same hormonal drivers, same treatments, plus standard dermatological care.
Weight. Where a woman carries excess weight, losing even five to ten percent frequently restores ovulation on its own. That is worth saying without shame attached, and it does not apply to everyone, since many Nigerian women with PCOS are not overweight at all.
Supplements. Inositol has modest evidence behind it, and some women with PCOS in Nigeria find it helpful. Treat it as support rather than treatment, and tell your doctor you are taking it.
Common questions
Questions about diagnosis
Do I need surgery to remove the cysts?
No. They are follicles, not cysts, and there is nothing to remove. Ovarian drilling is a different procedure used in selected fertility cases, decided by a specialist.
Can I have PCOS with regular periods?
Yes, if you meet two of the three criteria another way. Regular bleeding also does not always mean you are ovulating.
Will PCOS go away after I have a baby?
The fertility problem often improves. The metabolic part stays, which is why the checks above continue for life.
I am slim. Is it still PCOS?
Quite possibly. Obesity was less common in the PCOS group than the comparison group in the Nigerian series cited above.
Questions about treatment
Should I ask for letrozole instead of clomiphene?
It is a fair question to raise with your doctor, and the evidence supports asking. The prescribing decision stays with them.
Can I buy these drugs over the counter?
Please do not. Ovulation induction without scan monitoring risks multiple pregnancy and overstimulation, and both are avoidable.
Does PCOS in Nigeria mean I will need IVF?
No. Most women with PCOS who want to conceive do so with ovulation induction rather than IVF.
Is PCOS caused by eating too much sugar?
No. Insulin resistance is part of the condition rather than a punishment for diet, although what you eat affects how well you manage it.
Getting PCOS treatment in Nigeria without the guesswork
Living with PCOS in Nigeria asks for two things at once: the right medicine now, and a supply you can rely on for years afterwards.
That is where HubPharm Africa works. We source verified medicines through licensed channels, deliver across Nigeria, coordinate refills so treatment does not lapse, and put a pharmacist on the phone when a side effect makes you want to stop. When Nigerian pharmacies do not routinely stock a product, we tell you honestly whether we can source it and what the lead time looks like, rather than letting you hope. Across our programmes we have seen a 42 percent improvement in medication adherence and 95 percent patient satisfaction.
Bring your prescription and your questions. Both are welcome.
[Talk to a HubPharm pharmacist →]
⸻
This article is for general information and does not replace advice from your own doctor. Ovulation induction medicines require a prescription and monitoring, and nothing here should be started, changed or stopped without your doctor.
References
- Prevalence of polycystic ovary syndrome among infertile women attending a fertility clinic at a university teaching hospital in Nigeria.
- Legro RS et al. Letrozole versus clomiphene for infertility in the polycystic ovary syndrome. New England Journal of Medicine, 2014.
- International evidence-based guideline for the assessment and management of polycystic ovary syndrome.
- Rotterdam ESHRE and ASRM-sponsored PCOS consensus workshop group, revised diagnostic criteria.
- Aetiological pattern of infertility cases managed at the University of Ilorin Teaching Hospital, North-Central Nigeria.